
Short answer
Tesamorelin is an FDA-approved injection that signals the pituitary gland to release growth hormone. Sold as Egrifta, it has one approved use: reducing excess abdominal fat in adults with HIV and lipodystrophy. In two trials, 26 weeks of daily injections cut visceral belly fat by 18% and 14%. Body weight did not change. Any other use is off-label.
- What it is
- A synthetic analog of growth hormone-releasing factor (GHRH), injected under the skin once a day to raise the body's own growth hormone.
- FDA status
- FDA approved
Egrifta approved November 10, 2010 for excess abdominal fat in HIV-infected adults with lipodystrophy. Egrifta WR (11.6 mg vial) approved March 25, 2025. Egrifta SV and Egrifta WR are the two versions listed on DailyMed as of November 2, 2026.
- Evidence level
FDA label
Dosing comes from the FDA-approved prescribing information.
Tesamorelin is one of the few peptides people ask about that has a full FDA approval, two placebo-controlled phase 3 trials and a current label. That approval is narrow: excess abdominal fat in adults with HIV who have lipodystrophy, a condition in which fat shifts into the abdomen. Everything else people use it for, from general fat loss to anti-aging, is off-label. So the useful question is usually less “does it work?” than “does the evidence apply to me?” If you have HIV-related abdominal fat, it does. If you do not, you are relying on small trials and extrapolation.
| Your question | Short answer |
|---|---|
| What is it? | A synthetic version of growth hormone-releasing hormone, sold as Egrifta SV and Egrifta WR |
| Is it FDA-approved? | Yes, since November 10, 2010, for one use |
| Approved for what? | Reducing excess abdominal fat in HIV-infected adults with lipodystrophy |
| What did the trials show? | Visceral fat down 18% and 14% at 26 weeks; placebo groups changed by 2% or less |
| Does it cause weight loss? | No. The label calls it weight neutral and says it is not for weight loss |
| How is it given? | Once a day, injected under the skin of the abdomen |
| Main risks | Injection site reactions, fluid retention, higher blood sugar, raised IGF-1, allergic reactions |
| Who must not use it? | People with pituitary damage, active cancer, a known allergy to it, or a pregnancy |
What is tesamorelin?
Tesamorelin is a synthetic version of growth hormone-releasing factor (GRF, also called GHRH), the hormone the hypothalamus uses to tell the pituitary gland to release growth hormone. The label describes it as the full 44-amino-acid sequence of human GRF with a hexenoyl group, a short six-carbon chain, attached at the front end. A 2012 trial report calls it a stabilized GHRH analog. It is supplied as an acetate salt. It is not growth hormone itself, and it is not a steroid.
How does tesamorelin work?
Tesamorelin works through the pituitary, which then raises the body’s own growth hormone and, downstream, IGF-1 (insulin-like growth factor 1, the protein that carries out many of growth hormone’s effects). The label describes growth hormone as both anabolic and lipolytic, meaning it builds tissue and breaks down fat.
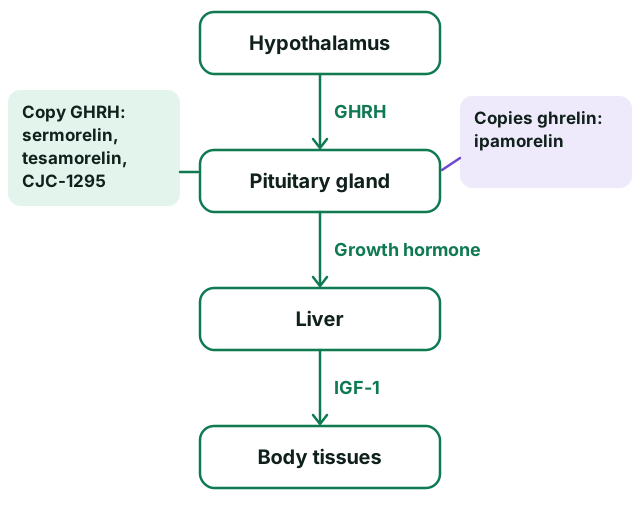
It depends on a working pituitary, and the label lists people whose pituitary has been removed or damaged as contraindicated. Absorption is low: the label puts bioavailability under the skin at less than 4%, and the half-life of the Egrifta WR dose at 11 minutes. The label reports no clinically significant changes in other pituitary hormones, including thyroid-stimulating hormone, in the trials.
Who is tesamorelin for?
Tesamorelin is for adults with HIV and lipodystrophy who have excess abdominal fat. That is the entire labeled use. The trials that supported it enrolled people aged 18 to 65 with a waist of at least 95 cm (37.4 inches) and a waist-to-hip ratio of at least 0.94 for men, or 94 cm (37.0 inches) and 0.88 for women. They were on stable antiretroviral treatment, and more than 80% were men in each trial.
The same trials left people out, which matters if you are trying to judge whether the results apply to you. They excluded a BMI of 20 or lower, type 1 diabetes, type 2 diabetes treated with insulin or other glucose-lowering drugs, a history of cancer, and hypopituitarism.
The label also limits the claim itself. Long-term cardiovascular safety has not been established, it is not for weight loss, and there are no data showing that it helps people stay on HIV treatment.
What are the benefits of tesamorelin?
The established benefit of tesamorelin is less visceral fat, the deep fat packed around the organs, in adults with HIV and lipodystrophy. Other benefits are smaller, less certain or limited to small studies.
| Benefit | What the evidence shows | Strength |
|---|---|---|
| Less visceral fat | Down 18% and 14% at 26 weeks, against +2% and -2% on placebo | FDA label, two phase 3 trials |
| Smaller waist | Down 3 cm and 2 cm, against 1 cm on placebo in each study | FDA label |
| Less trunk fat | Down 1.0 kg and 0.8 kg | FDA label |
| More lean body mass | Up 1.3 kg and 1.2 kg | FDA label |
| Less distress about belly appearance | People rated it improved | FDA label |
| Lower triglycerides | Down 50 mg/dL vs up 9 mg/dL in the first trial | NEJM 2007 |
| Less liver fat | 37% relative reduction in adults with HIV and fatty liver | One 61-person trial |
| Better thinking and memory | Better executive function scores in older adults | One 152-person trial |
| Fat loss in people without HIV | We found no large trial | Not established |
| Muscle gain, anti-aging | We found no trial testing these as goals | Not established |
Two meta-analyses published in 2026 pooled the HIV trials and agree with the headline result. Ditta and colleagues, with 4 trials and 909 people, found visceral fat down 21.47 cm² against placebo, waist down 1.61 cm and lean mass up 1.42 kg, with no significant change in the fat just under the skin. Badran and colleagues, with 5 trials, found visceral fat down 27.71 cm². Both cover people with HIV, so neither widens the evidence beyond them.
What the trials showed
The approval rests on two 26-week randomized, double-blind trials in adults with HIV and excess abdominal fat, each followed by a 26-week extension. Everyone received 2 mg of the original formulation or placebo once a day, and the main measure was visceral adipose tissue (VAT), the fat packed around the organs, measured by CT scan at the level of the lower spine. These numbers come from the current Egrifta WR label.
| Measure at week 26 | Study 1: tesamorelin (n=273) | Study 1: placebo (n=137) | Study 2: tesamorelin (n=270) | Study 2: placebo (n=126) |
|---|---|---|---|---|
| Visceral fat, change | -27 cm² | +4 cm² | -21 cm² | 0 cm² |
| Visceral fat, % change | -18% | +2% | -14% | -2% |
| IGF-1, change | +107 ng/mL | -15 ng/mL | +108 ng/mL | +3 ng/mL |
| Body weight, change | -0.4 kg | 0.0 kg | +0.5 kg | +0.3 kg |
| Waist, change | -3 cm | -1 cm | -2 cm | -1 cm |
Study 1 was published in the New England Journal of Medicine in 2007. Its paper reports visceral fat down 15.2% on tesamorelin versus up 5.0% on placebo, triglycerides down 50 mg/dL versus up 9 mg/dL, and IGF-1 up 81%. The pooled analysis of both trials, 806 people in all, published in the Journal of Clinical Endocrinology and Metabolism in 2010, reports a treatment effect of -15.4% on visceral fat with no meaningful change in the fat just under the skin of the abdomen. The percentages differ slightly between the papers and the label, partly because the label’s percentages come from a statistical model rather than raw averages; the direction and rough size are the same.
How long does tesamorelin take to work?
Tesamorelin was measured at 26 weeks, and that is the timeframe the evidence supports. IGF-1 moved sooner: the label reports high levels as early as week 13. The 2026 Ditta meta-analysis found the visceral fat reduction was significant only in trials lasting 26 weeks or longer, so a few weeks on the drug is too short to judge it. The label says to weigh continuing in anyone whose visceral fat has not come down.
What happens when it stops
At week 26, people on tesamorelin were re-randomized to keep going or switch to placebo. Those who switched lost the benefit. In Study 1, visceral fat rose 22% over the next 26 weeks after switching, versus no change in those who stayed on tesamorelin. In Study 2 the figures were +16% after switching versus -5% when continuing. So the effect lasted only as long as treatment did.
The formulations
There have been three Egrifta products. The label for each one says they differ in dose, number of vials, mixing and storage, and the two current labels state that Egrifta WR and Egrifta SV “are not substitutable.”
| Product | Vial | Mixed with | Label daily dose | Volume per dose | Status |
|---|---|---|---|---|---|
| Egrifta (original) | 1 mg | Sterile Water for Injection | 2 mg (two vials) | Not applicable today | Approved 2010; not listed on DailyMed |
| Egrifta SV | 2 mg | 0.5 mL Sterile Water for Injection | 1.4 mg | 0.35 mL | Listed on DailyMed (July 31, 2026 version) |
| Egrifta WR | 11.6 mg | 1.3 mL Bacteriostatic Water for Injection | 1.28 mg | 0.16 mL | Approved March 25, 2025; listed on DailyMed (August 3, 2026 version) |
Egrifta SV is mixed fresh for every dose and the leftover is thrown away. Egrifta WR is mixed once a week: one vial gives seven daily doses and is discarded seven days after mixing. The manufacturer announced Egrifta WR’s availability on September 5, 2025 and said it “will gradually replace” Egrifta SV, which stays available during a transition period. We found no announced end date for that period. The lower WR dose is not a weaker treatment: the label says 1.28 mg of Egrifta WR produces similar blood levels to 2 mg of the original formulation, which is the dose the trials used.
The tesamorelin dosage guide has the mixing steps and syringe volumes, and the tesamorelin calculator shows the label doses in units.
Tesamorelin off-label: what the evidence shows
Interest in tesamorelin outside HIV lipodystrophy has grown alongside interest in peptides generally, but no off-label use has been shown in large trials. A few uses have been tested in randomized trials. None is FDA-approved, and each trial was small.
| Use | Trial | Who | What was given | What was found |
|---|---|---|---|---|
| Liver fat | Stanley et al. 2014, JAMA | 50 adults with HIV and abdominal fat | 2 mg daily or placebo, 6 months | Visceral fat -34 cm² vs +8 cm²; liver fat fell modestly (median -2.0% vs +0.9% lipid to water) |
| Fatty liver disease (NAFLD) | Stanley et al. 2019, Lancet HIV | 61 adults with HIV and liver fat of 5% or more | 2 mg daily or placebo, 12 months | Liver fat fell 4.1 percentage points more than placebo, a 37% relative reduction; 35% vs 4% reached under 5% |
| Thinking and memory | Baker et al. 2012, Arch Neurol | 152 adults aged 55 to 87, some with mild cognitive impairment | 1 mg daily or placebo, 20 weeks | Better scores on executive function tests; IGF-1 up 117%; adverse events in 68% vs 36% |
These studies show real signals worth further research. They do not show that tesamorelin is safe or useful for people without HIV, for longer than a year, or for general fat loss, muscle or anti-aging. Each of those uses would still be off-label. The Baker trial also recorded a 35% rise in fasting insulin, still within the normal range, in its group with mild cognitive impairment.
Off-label prescribing of an approved drug is legal. It also means the prescriber and patient are working without the label’s evidence, and that the label’s safety numbers came from a different population.
What are the side effects of tesamorelin?
The most common side effects of tesamorelin are injection site reactions, in 17% versus 6% on placebo, and joint pain, in 13% versus 11%. Muscle aches, swelling and tingling or numbness were also more frequent, and most of that group traces to fluid retention. The label’s warnings go further: 47% of people had IGF-1 more than 2 standard deviation scores above normal at 26 weeks, 5% versus 1% reached a diabetes-range HbA1c, and 4% had allergic reactions. The full table and the warning signs are in tesamorelin side effects.
What does tesamorelin cost?
Egrifta SV costs about $2,610 cash for 30 of the 2 mg vials, roughly one month, according to the Drugs.com price guide. That is a pharmacy cash figure and is not valid with insurance. We found no equivalent reference price for Egrifta WR, and most of the other prices online come from sellers.
Egrifta is dispensed through specialty pharmacies, and the manufacturer’s THERA patient support program helps with insurance checks. Its page describes three routes:
| Your situation | What the program describes |
|---|---|
| Commercial or employer insurance | You may be eligible for a co-pay assistance program |
| Government insurance | Information and resources that may lower out-of-pocket costs |
| Qualifying patients | A patient assistance program offering the medicine at no cost |
Terms and eligibility are set by the program, and the phone number on the Egrifta site is 1-833-23-THERA. For off-label use, we found no published coverage policy we could cite, so check with your plan before assuming it will pay.
Can tesamorelin be compounded?
Tesamorelin generally cannot be compounded under the usual rules. Its application was moved from a new drug application to a biologics license application (BLA) on March 23, 2020, when FDA reclassified a group of protein products as biological products. FDA’s notice to compounders that month states that these transitioned products “will not be eligible for the exemptions in sections 503A and 503B,” the sections that let pharmacies and outsourcing facilities compound drugs. That makes Egrifta SV and Egrifta WR, prescribed for the labeled use, the legitimate routes to tesamorelin in the United States.
Tesamorelin is also not on the interim HHS policy announced October 28, 2026, in which HHS says it does not intend to take enforcement action against 503A compounding of six other peptides when ten conditions are met. None of those six is FDA-approved, and as of November 2, 2026 the policy does not change tesamorelin’s position.
Vials sold online as tesamorelin “for research use only” are a different thing. Under 21 CFR 312.160, a research-only product may be shipped only for tests in laboratory animals or in test tubes, labeled “Not for use in humans.” Those products are not legal to use on people, and they carry no FDA-verified identity, purity or sterility. The FDA status tracker shows how this applies across peptides.
How does tesamorelin compare with similar drugs?
Tesamorelin and sermorelin copy the same hormone, but only tesamorelin has a current approval and large placebo-controlled trials. Sermorelin is a shorter fragment with no approved product today, and sermorelin vs tesamorelin lays out the differences. No trial has compared them. GLP-1 drugs are a separate class that includes drugs approved for weight loss, which tesamorelin is not.
Questions to ask a prescriber
- Am I in the population the label covers? If not, what evidence are you relying on?
- Which product are you prescribing, SV or WR, and who will train me to mix it?
- When will my glucose, HbA1c and IGF-1 be checked?
- How does my cancer history affect this?
- How will we measure whether visceral fat has come down, and when will we decide whether to continue?
- What is the plan if I stop, given that the fat came back in the trials?
Tesamorelin in sport
The World Anti-Doping Agency’s Prohibited List names tesamorelin as an example under S2.2.4, growth hormone-releasing hormone and its analogues. Class S2 is prohibited at all times, in and out of competition. A prescription does not change that without a therapeutic use exemption.
Who should not use it
The label lists four contraindications:
- Disruption of the hypothalamic-pituitary axis from pituitary removal, hypopituitarism, a pituitary tumor or surgery, head radiation or head trauma.
- Active cancer. Any previous cancer should be inactive and its treatment complete.
- Known allergy to tesamorelin or its inactive ingredients.
- Pregnancy. Rat studies found hydrocephaly in offspring, and the label says reducing visceral fat offers no benefit during pregnancy.
The label also warns about raised IGF-1, fluid retention, glucose intolerance and diabetes, allergic reactions, injection site reactions and increased deaths in acute critical illness, and it says to stop if cancer returns. People with HIV are told not to breastfeed, and it is not for children.
Compare
- PeptidesFDA approvedDosageThe label dose of tesamorelin is 1.4 mg (0.35 mL) of Egrifta SV or 1.28 mg (0.16 mL) of Egrifta WR once daily.
- PeptidesFDA approvedSide effectsThe most common tesamorelin side effects are injection site reactions (17%) and joint pain (13%).
- PeptidesCompounded (Rx)Vs tesamorelinTesamorelin has FDA approval and two large trials, for HIV-related belly fat only.
Peptide news, sorted. Plus the printable dose chart.
Sorted, every Tuesday: the week's peptide and GLP-1 news in five minutes: FDA moves, new studies explained, and price changes. Subscribe and the one-page dose and injection-site chart arrives first.
Questions people ask
Is tesamorelin FDA-approved?
Is tesamorelin a weight-loss drug?
Can you take tesamorelin without HIV?
Does the fat come back after stopping?
Can a pharmacy compound tesamorelin?
What is the difference between tesamorelin and sermorelin?
Sources
Primary sources first: FDA labels and documents, peer-reviewed trials, registries.
- 1Egrifta WR (tesamorelin) for injection, 11.6 mg/vial, prescribing information, Theratechnologies, revised 3/2025, via FDAaccessdata.fda.gov
- 2Egrifta SV (tesamorelin) for injection, 2 mg/vial, prescribing information, Theratechnologies, revised 2/2024, via FDAaccessdata.fda.gov
- 3DailyMed. Egrifta WR (tesamorelin) kit, SPL version 2, published August 3, 2026dailymed.nlm.nih.gov
- 4DailyMed. Egrifta SV (tesamorelin) kit, SPL version 9, published July 31, 2026dailymed.nlm.nih.gov
- 5Egrifta (tesamorelin for injection), 1 mg/vial, original prescribing information, November 2010, via FDAaccessdata.fda.gov
- 6Drugs@FDA. Egrifta (tesamorelin), BLA 022505, approved November 10, 2010; deemed a BLA March 23, 2020accessdata.fda.gov
- 7Theratechnologies. Announces availability of Egrifta WR, September 5, 2025 (via Nasdaq)nasdaq.com
- 8THERA patient support program, manufacturer page for Egrifta WR, checked November 2, 2026egriftawr.com
- 9Drugs.com. Egrifta prices, cash price guide, checked November 2, 2026drugs.com
- 10Falutz J et al. Metabolic effects of a growth hormone-releasing factor in patients with HIV. N Engl J Med 2007pubmed.ncbi.nlm.nih.gov
- 11Falutz J et al. Effects of tesamorelin in HIV-infected patients with abdominal fat accumulation: a randomized placebo-controlled trial with a safety extension. J Acquir Immune Defic Syndr 2010pubmed.ncbi.nlm.nih.gov
- 12Falutz J et al. Effects of tesamorelin: a pooled analysis of two phase 3 trials with safety extension data. J Clin Endocrinol Metab 2010pubmed.ncbi.nlm.nih.gov
- 13Stanley TL et al. Effect of tesamorelin on visceral fat and liver fat in HIV-infected patients with abdominal fat accumulation. JAMA 2014pubmed.ncbi.nlm.nih.gov
- 14Stanley TL et al. Effects of tesamorelin on non-alcoholic fatty liver disease in HIV: a randomised, double-blind, multicentre trial. Lancet HIV 2019pubmed.ncbi.nlm.nih.gov
- 15Baker LD et al. Effects of growth hormone-releasing hormone on cognitive function in adults with mild cognitive impairment and healthy older adults. Arch Neurol 2012pubmed.ncbi.nlm.nih.gov
- 16Badran AS et al. Body composition, hepatic fat, metabolic, and safety outcomes of tesamorelin in HIV-associated lipodystrophy: a meta-analysis of randomized controlled trials. Obes Res Clin Pract 2026pubmed.ncbi.nlm.nih.gov
- 17Ditta AM et al. Efficacy and safety of tesamorelin in people living with HIV with lipodystrophy: a systematic review and meta-analysis. J Int Assoc Provid AIDS Care 2026pmc.ncbi.nlm.nih.gov
- 18FDA. Notice to compounders: changes that affect compounding on March 23, 2020fda.gov
- 19HHS. Enforcement Discretion Policy Regarding 503A Compounding Using Certain Peptide Bulk Drug Substances, with Appendices A and B, October 2026hhs.gov
- 20Federal Register. Notice of availability, FR Doc. 2026-22192, Docket HHS-OASH-2026-0496, RIN 0910-ZD94, published October 30, 2026public-inspection.federalregister.gov
- 21Federal Register. Determination that Geref (sermorelin acetate) injection was not withdrawn from sale for reasons of safety or effectiveness, March 4, 2013public-inspection.federalregister.gov
- 2221 CFR 312.160, drugs for investigational use in laboratory research animals or in vitro testslaw.cornell.edu
- 23WADA. The Prohibited List (current)wada-ama.org
- 24Finnish Center for Integrity in Sports (SUEK). Doping agent classes and substances 2026 (S2.2.4 GHRH analogues)kamu.suek.fi
Go deeper on Tesamorelin
- DosageThe label dose of tesamorelin is 1.4 mg (0.35 mL) of Egrifta SV or 1.28 mg (0.16 mL) of Egrifta WR once daily. Mixing, units, timing and missed doses.Read
- Side effectsThe most common tesamorelin side effects are injection site reactions (17%) and joint pain (13%). Label rates, blood sugar risks, and when to call.Read
PeptideSorted Editorial Team
Editorial review
The PeptideSorted editors check every guide against its cited sources before publication: each number against its FDA label, trial or registry, the FDA status against current FDA and HHS documents, and the wording against our describe-never-prescribe rule. Licensed clinicians who join the review panel are listed by name on the editorial team page.
This page was checked against its cited sources by the PeptideSorted editorial team. Licensed clinicians on our review panel are listed on the editorial team page. Every health page cites primary sources and shows its review date. Read the editorial policy and how medical review works, or report an error via corrections. Educational only; not medical advice.