Short answer
CJC-1295 and ipamorelin are two unapproved peptides that raise growth hormone through different receptors, and no published trial has tested them together. Each had small human studies between 1999 and 2014 and was dropped before approval. FDA's advisers voted against compounding both in 2024, no human dose is established, and WADA bans both.
- What it is
- Two different peptides often sold together: CJC-1295, a modified growth hormone-releasing hormone, and ipamorelin, a ghrelin-receptor agonist.
- FDA status
- Not FDA approved
Neither is FDA-approved. Both were placed in 503A category 2 on September 29, 2023; the PCAC voted against adding ipamorelin (October 29, 2024) and CJC-1295 (December 4, 2024) to the bulks list; neither is on any 503A list, and neither is covered by HHS's October 2026 enforcement policy.
- Evidence level
Early human studies
Small or uncontrolled human studies only.
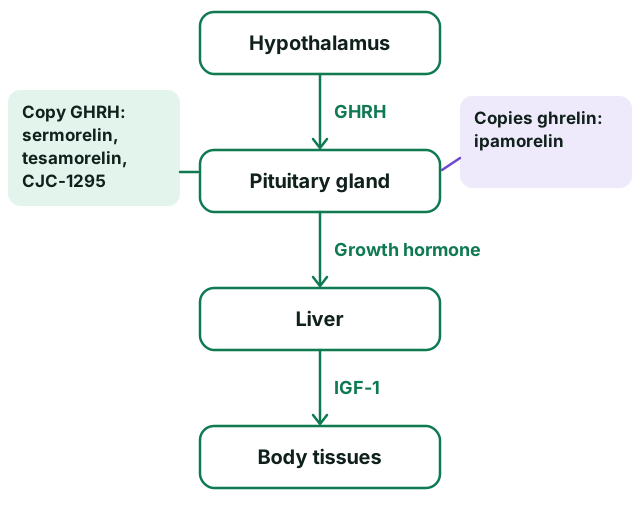
CJC-1295 and ipamorelin are two different peptides, usually sold as a pair and often in the same vial, and no published trial has ever tested them together. Both make the pituitary gland release growth hormone, through different receptors. Each had a short run as a pharmaceutical candidate and was dropped before approval. Neither is FDA-approved, neither is on any list that lets pharmacies compound it, and vials labeled “for research use only” are not legal to use on people. If you came for one peptide on its own, the ipamorelin guide covers that side in depth, and this page carries the detail on CJC-1295 and on the pairing.
| Question | CJC-1295 | Ipamorelin | The two together |
|---|---|---|---|
| What it copies | Growth hormone-releasing hormone (GHRH) | Ghrelin | Both signals at once |
| Published human data | Two 2006 hormone studies in healthy adults | One small dose study and one phase 2 surgery trial | None found |
| Route in those studies | Under the skin, once or a few times | Into a vein | Not applicable |
| Muscle, fat or sleep measured? | No | No | No |
| FDA-approved? | No | No | No |
| FDA advisers’ vote | Against, December 2024 | Against, October 2024 | Not reviewed as a pair |
| WADA | Banned | Banned | Banned |
What is CJC-1295?
CJC-1295 is a lab-made version of growth hormone-releasing hormone, the brain’s signal telling the pituitary to release growth hormone. Natural GHRH is cleared from the blood quickly, which limits its use as a drug. CJC-1295 starts from the first 29 amino acids of GHRH, with four amino acids swapped to resist breakdown.
The version tested in people by its developer, the Montreal company ConjuChem, adds a DAC (drug affinity complex): a lysine linker carrying a reactive chemical that binds permanently to albumin, the main protein in blood. At least 90% of the injected peptide binds this way. In the 2006 study the estimated half-life was 5.8 to 8.1 days.
The version sold as “CJC-1295 without DAC”, also called modified GRF (1-29), is the same modified fragment without the albumin linker. We found no published human trial of this version, so nearly everything claimed about it is borrowed from the DAC version or from guesswork. That matters because the without-DAC form is the one most often paired with ipamorelin online. When FDA’s advisory committee reviewed CJC-1295 in December 2024, it voted on both forms.
What is ipamorelin?
Ipamorelin is a five-amino-acid peptide (a pentapeptide) developed at Novo Nordisk and described in 1998. It works on a different receptor: the ghrelin receptor, also called the growth hormone secretagogue receptor. Ghrelin is a hormone from the stomach that also triggers growth hormone release. In pigs, ipamorelin released growth hormone without raising the stress hormones ACTH and cortisol, even at doses more than 200 times the effective dose. In healthy men it had a half-life of about 2 hours.
Why are they sold together?
The pitch is that pressing two switches at once releases more growth hormone than pressing either alone. That is an extrapolation from physiology. We found no published human trial that tested CJC-1295 and ipamorelin together, measured the combined effect, or checked the safety of the pair.
There is also a mismatch at the center of the pairing. The tested CJC-1295 lasted about a week. The ipamorelin pulse was over within hours. The form usually paired, CJC-1295 without DAC, has no published human data at all, so the case for it is theory stacked on theory.
What the human studies found
| Study | Who | What was given | What was found |
|---|---|---|---|
| Teichman et al. 2006, JCEM (CJC-1295 with DAC) | Healthy adults aged 21 to 61, in two randomized placebo-controlled trials | Single injections under the skin of 30, 60, 125 or 250 mcg/kg; or two or three injections of 20 to 60 mcg/kg, a week or two weeks apart | Growth hormone rose 2- to 10-fold for 6 days or more; IGF-1 rose 1.5- to 3-fold for 9 to 11 days; with repeated doses IGF-1 stayed above baseline for up to 28 days. No serious adverse reactions |
| Ionescu and Frohman 2006, JCEM (CJC-1295 with DAC) | Healthy men aged 20 to 40 | One injection of 60 or 90 mcg/kg | A week later, the normal pulses of growth hormone were preserved; trough growth hormone rose 7.5-fold, average growth hormone 46% and IGF-1 45% |
| Gobburu et al. 1999, Pharm Res (ipamorelin) | Healthy men, 8 per dose level | One 15-minute intravenous infusion at five dose levels | A single burst of growth hormone peaking at about 40 minutes at every dose; half-life about 2 hours |
| Beck et al. 2014, Int J Colorectal Dis (ipamorelin, NCT00672074) | 117 adults after bowel resection surgery | 0.03 mg/kg intravenously twice daily for up to 7 days, or placebo | Median time to first tolerated meal 25.3 hours versus 32.6 hours on placebo, not statistically significant (p = 0.15). Adverse events in 87.5% versus 94.8% on placebo |
| Helsinn phase 2 dose-finding trial (ipamorelin, NCT01280344) | 320 adults after bowel resection | Three dose levels versus placebo | Completed in 2014; no results posted on ClinicalTrials.gov |
IGF-1 (insulin-like growth factor 1) is the hormone the liver makes in response to growth hormone, and it carries many of growth hormone’s effects. None of these studies measured muscle, fat loss, sleep, recovery or any of the outcomes the pair is marketed for. They measured hormone levels, or, for ipamorelin, bowel recovery after surgery.
What results can you expect from CJC-1295 and ipamorelin?
Nobody knows, because no trial has measured a result a person would notice, on any timeline. Claims about leaner bodies at 12 weeks or better sleep in the first month come from clinics and forums. Higher hormone numbers are not the same as better outcomes. Growth hormone itself adds lean mass in fit adults without adding strength, as the guide to peptides for muscle growth shows.
The same goes for dosing. No human dose of either peptide has been established. The CJC-1295 and ipamorelin dosage page lists what the studies actually gave and why the daily schedules seen online do not follow from them.
Why development stopped
CJC-1295. ConjuChem’s phase 2 trial was testing 12 weeks of low-dose or high-dose CJC-1295 against placebo in people with HIV and excess visceral (deep belly) fat. In July 2006 the company halted dosing after a participant died at a clinical site in Argentina. The company said at the time that the cause of death and its relationship to the study drug were under investigation. The trial is listed as terminated, no later trial results for CJC-1295 have been published, and it never reached FDA approval.
Ipamorelin. Helsinn tested intravenous ipamorelin to speed recovery of bowel function after surgery. The first phase 2 trial found no significant difference from placebo on its key or secondary outcomes. A larger dose-finding trial finished in 2014 and has posted no results. Ipamorelin was never approved by FDA.
CJC-1295 and ipamorelin side effects
Short-term reactions are documented for each peptide alone. Nothing is documented for the pair, and no study has followed people on either for months.
| Reaction | Where it was seen | How often |
|---|---|---|
| Injection site reactions | CJC-1295, 2006 study | About 70% of treated subjects |
| Headache | CJC-1295, 2006 study | 63% |
| Diarrhea | CJC-1295, 2006 study | 43% |
| Flushing, warmth or a brief drop in blood pressure | CJC-1295, 2006 study, after a single dose | 30%, more often at higher doses |
| Low potassium | Ipamorelin, after bowel surgery | 12.5% versus 3.4% on placebo |
| Insomnia | Ipamorelin, after bowel surgery | 10.7% versus 5.2% on placebo |
| High blood sugar at discharge | Ipamorelin, after bowel surgery | 14.3% versus 8.6% on placebo |
FDA’s safety-risk page reports “serious adverse events associated with CJC-1295 including increased heart rate and systemic vasodilatory reaction,” notes that clinical data are limited, and raises concerns about immune reactions. For ipamorelin it says a published study “identified serious adverse events including death when ipamorelin was administered intravenously.” That study was the bowel surgery trial: two people on ipamorelin died of complications after colon cancer surgery, and FDA said it is unclear whether the deaths were related to the drug.
Keep these in view too:
- Long-term effects are unknown. Prolonged high IGF-1 is a concern with approved growth hormone-releasing drugs: the tesamorelin label says the effects of prolonged IGF-1 elevation “are unknown” and tells prescribers to monitor it.
- Cancer history. Growth hormone and IGF-1 are growth factors. The approved drug in this class, tesamorelin, is contraindicated in active malignancy.
- Blood sugar and fluid. Growth hormone raises blood sugar and can cause fluid retention, joint pain and carpal tunnel symptoms, which the tesamorelin label lists.
- Pregnancy. Tesamorelin is contraindicated in pregnancy, and FDA notes animal data suggesting harm to fertility and fetal development from ghrelin itself.
- Two peptides in one vial. A reaction cannot be traced to one ingredient, and a blend cannot be adjusted one peptide at a time.
Get prompt medical care for hives, widespread rash or trouble breathing after an injection, for a severe headache with vision changes, or for unusual thirst and frequent urination. Tell the clinician exactly what you injected.
FDA status
Neither peptide is approved, and neither has a lawful route to compounding under section 503A, the part of federal law covering pharmacy compounding for individual patients.
| Date | What happened |
|---|---|
| September 29, 2023 | FDA placed CJC-1295 and ipamorelin acetate in 503A category 2, substances that raise significant safety risks. Ipamorelin acetate was also placed in category 2 for 503B outsourcing facilities |
| October 29, 2024 | FDA’s Pharmacy Compounding Advisory Committee (PCAC) reviewed ipamorelin and ipamorelin acetate for growth hormone deficiency and postoperative ileus. FDA proposed against listing. The committee voted 0 yes, 12 no, 1 abstain on each form, citing a lack of information supporting safety and efficacy |
| December 4, 2024 | The PCAC reviewed five forms of CJC-1295, with and without DAC, for growth hormone deficiency. FDA proposed against listing. The votes were 0 yes and 13 no for four forms, and 1 yes and 12 no for CJC-1295 acetate. One member cited the lack of evidence for effectiveness |
| By April 2026 | FDA’s safety-risk page lists CJC-1295 and ipamorelin acetate under substances whose nominations were withdrawn. Ipamorelin acetate is still listed in 503B category 2 |
| May 14, 2026 | Neither appears in any category on FDA’s 503A list, and neither is on the 503A bulks list |
| October 30, 2026 | HHS published an enforcement policy covering six other peptides. CJC-1295 and ipamorelin are not on its list |
If you have read that peptides became available again in October 2026, that does not apply here. As of November 2, 2026, HHS says it does not intend to take enforcement action over compounding of six named peptides, when each is compounded alone and other conditions are met. Neither CJC-1295 nor ipamorelin is one of the six, and the policy’s single-ingredient condition would rule out a two-peptide vial in any case.
The practical result: no pharmacy may lawfully compound either peptide under section 503A, and products sold as research chemicals are unapproved new drugs. Under 21 CFR 312.160, a company may ship an unapproved drug only for tests in laboratory animals or in test tubes, with a label reading “Not for use in humans.” FDA warning letters to peptide sellers, including one in March 2026, have found that the disclaimer does not protect a seller whose marketing shows the product is meant for people.
Are CJC-1295 and ipamorelin banned in sport?
Yes. Both are prohibited at all times under class S2 of the World Anti-Doping Agency’s Prohibited List. Section S2.2.4 names CJC-1295 as an example of a growth hormone-releasing hormone analogue (alongside sermorelin and tesamorelin) and ipamorelin as an example of a growth hormone secretagogue (alongside ibutamoren and macimorelin). The 2027 list, in effect January 1, 2027, keeps both entries.
How the pair compares with what is approved
The nearest approved drug is tesamorelin, which works on the same receptor as CJC-1295 and has phase 3 trials, a label and one approved use: reducing excess abdominal fat in HIV-associated lipodystrophy. The head-to-head framing in ipamorelin vs tesamorelin shows the gap in evidence. Sermorelin is the older GHRH fragment that was once an approved drug, and MK-677 is the oral drug that uses ipamorelin’s receptor.
Questions to ask a prescriber
No approved product exists for either peptide, so there is no labeled price or insurance route to compare. If a clinic offers this pair, ask:
- Which version of CJC-1295 is this, with or without DAC, and what human data support that version?
- Who made this product, and on what legal basis is it supplied, given that neither peptide is on the 503A bulks list?
- Has my growth hormone or IGF-1 been tested, and what would count as a result?
- What monitoring will you do for blood sugar, IGF-1 and side effects?
- Does my cancer history, diabetes risk or pregnancy plan change this?
- Is there an approved option for the problem I actually have?
Compare
- PeptidesNot FDA approvedIpamorelinIpamorelin triggers a growth hormone pulse, but no benefit is proven in people.
- PeptidesNot FDA approvedDosageNo daily dose of CJC-1295 or ipamorelin has been tested.
- PeptidesNot FDA approvedIpamorelin vs tesamorelinTesamorelin is FDA-approved with phase 3 data for one use.
Peptide news, sorted. Plus the printable dose chart.
Sorted, every Tuesday: the week's peptide and GLP-1 news in five minutes: FDA moves, new studies explained, and price changes. Subscribe and the one-page dose and injection-site chart arrives first.
Questions people ask
Is CJC-1295 with ipamorelin FDA-approved?
Has the combination been tested in people?
What is the difference between CJC-1295 with and without DAC?
What are the side effects of CJC-1295?
Are CJC-1295 and ipamorelin banned in sport?
Why did development stop?
Sources
Primary sources first: FDA labels and documents, peer-reviewed trials, registries.
- 1Teichman SL et al. Prolonged stimulation of growth hormone (GH) and insulin-like growth factor I secretion by CJC-1295, a long-acting analog of GH-releasing hormone, in healthy adults. J Clin Endocrinol Metab 2006pubmed.ncbi.nlm.nih.gov
- 2Ionescu M, Frohman LA. Pulsatile secretion of growth hormone (GH) persists during continuous stimulation by CJC-1295, a long-acting GH-releasing hormone analog. J Clin Endocrinol Metab 2006pubmed.ncbi.nlm.nih.gov
- 3Raun K et al. Ipamorelin, the first selective growth hormone secretagogue. Eur J Endocrinol 1998pubmed.ncbi.nlm.nih.gov
- 4Gobburu JV et al. Pharmacokinetic-pharmacodynamic modeling of ipamorelin, a growth hormone releasing peptide, in human volunteers. Pharm Res 1999pubmed.ncbi.nlm.nih.gov
- 5Beck DE et al. Prospective, randomized, controlled, proof-of-concept study of the ghrelin mimetic ipamorelin for the management of postoperative ileus in bowel resection patients. Int J Colorectal Dis 2014pubmed.ncbi.nlm.nih.gov
- 6ClinicalTrials.gov NCT00672074. Phase 2 study of ipamorelin for postoperative ileus (Helsinn)clinicaltrials.gov
- 7ClinicalTrials.gov NCT01280344. Phase 2 dose-finding study of ipamorelin for recovery of gastrointestinal function after bowel resection (Helsinn)clinicaltrials.gov
- 8ClinicalTrials.gov NCT00267527. Phase 2 study of CJC 1295 in HIV patients with visceral obesity (ConjuChem), terminatedclinicaltrials.gov
- 9Fierce Biotech. ConjuChem shares dive on study death, July 13, 2006fiercebiotech.com
- 10aidsmap. Lipodystrophy study halted after patient death, July 31, 2006aidsmap.com
- 11FDA. Final summary minutes, Pharmacy Compounding Advisory Committee, October 29, 2024 (ipamorelin)fda.gov
- 12FDA. Final summary minutes, Pharmacy Compounding Advisory Committee, December 4, 2024 (CJC-1295)fda.gov
- 13FDA. Briefing document on ipamorelin-related bulk drug substances, Pharmacy Compounding Advisory Committee, October 29, 2024fda.gov
- 14FDA. Briefing document, Pharmacy Compounding Advisory Committee, December 4, 2024 (FDA's proposals on CJC-1295)fda.gov
- 15FDA. Certain bulk drug substances for use in compounding may present significant safety risks (content current as of April 22, 2026)fda.gov
- 16FDA. Bulk drug substances nominated for use in compounding under section 503A, category list (updated May 14, 2026)fda.gov
- 17FDA. 503A categories update, September 29, 2023 (copy hosted by the Alliance for Pharmacy Compounding)join.a4pc.org
- 18HHS. Enforcement Discretion Policy Regarding 503A Compounding Using Certain Peptide Bulk Drug Substances, with Appendices A and B, October 2026hhs.gov
- 19Federal Register. Notice of availability, FR Doc. 2026-22192, Docket HHS-OASH-2026-0496, RIN 0910-ZD94, published October 30, 2026public-inspection.federalregister.gov
- 20WADA. 2027 Prohibited List, in effect January 1, 2027wada-ama.org
- 21WADA 2026 Prohibited List, official text as reprinted in the Dutch Treaty Series (Trb. 2026, 25)zoek.officielebekendmakingen.nl
- 22WADA. The Prohibited List (current)wada-ama.org
- 23EGRIFTA WR (tesamorelin) prescribing information, revised March 2025, via FDAaccessdata.fda.gov
- 24SEROSTIM (somatropin) prescribing information, via DailyMeddailymed.nlm.nih.gov
- 25CDC. Diabetes symptomscdc.gov
- 2621 CFR 312.160, drugs for investigational use in laboratory research animals or in vitro testslaw.cornell.edu
- 27FDA warning letter to Gram Peptides, March 31, 2026fda.gov
Go deeper on CJC-1295 / Ipamorelin
- DosageNo daily dose of CJC-1295 or ipamorelin has been tested. What the human studies gave, by what route and how often, and why online protocols do not follow.Read
- Ipamorelin vs tesamorelinTesamorelin is FDA-approved with phase 3 data for one use. Ipamorelin is unapproved and was only ever given by vein. A side-by-side look at both.Read
PeptideSorted Editorial Team
Editorial review
The PeptideSorted editors check every guide against its cited sources before publication: each number against its FDA label, trial or registry, the FDA status against current FDA and HHS documents, and the wording against our describe-never-prescribe rule. Licensed clinicians who join the review panel are listed by name on the editorial team page.
This page was checked against its cited sources by the PeptideSorted editorial team. Licensed clinicians on our review panel are listed on the editorial team page. Every health page cites primary sources and shows its review date. Read the editorial policy and how medical review works, or report an error via corrections. Educational only; not medical advice.